

Heavy Metal Testing: Blood, Urine, Hair, and Provocation Tests Compared
Explore the clinic directoryIn this article
Heavy Metal Testing: Which Test Do You Actually Need?
Heavy metal testing measures toxic metals such as lead, mercury, arsenic and cadmium in a sample of blood, urine or hair, and the right test depends on the metal: whole blood is the standard test for lead and for mercury from fish, while urine is the preferred specimen for arsenic and inorganic mercury. Hair analysis and provoked (chelation challenge) urine tests are far less reliable, and the American College of Medical Toxicology (2010) advises against judging provoked results against ordinary reference ranges.
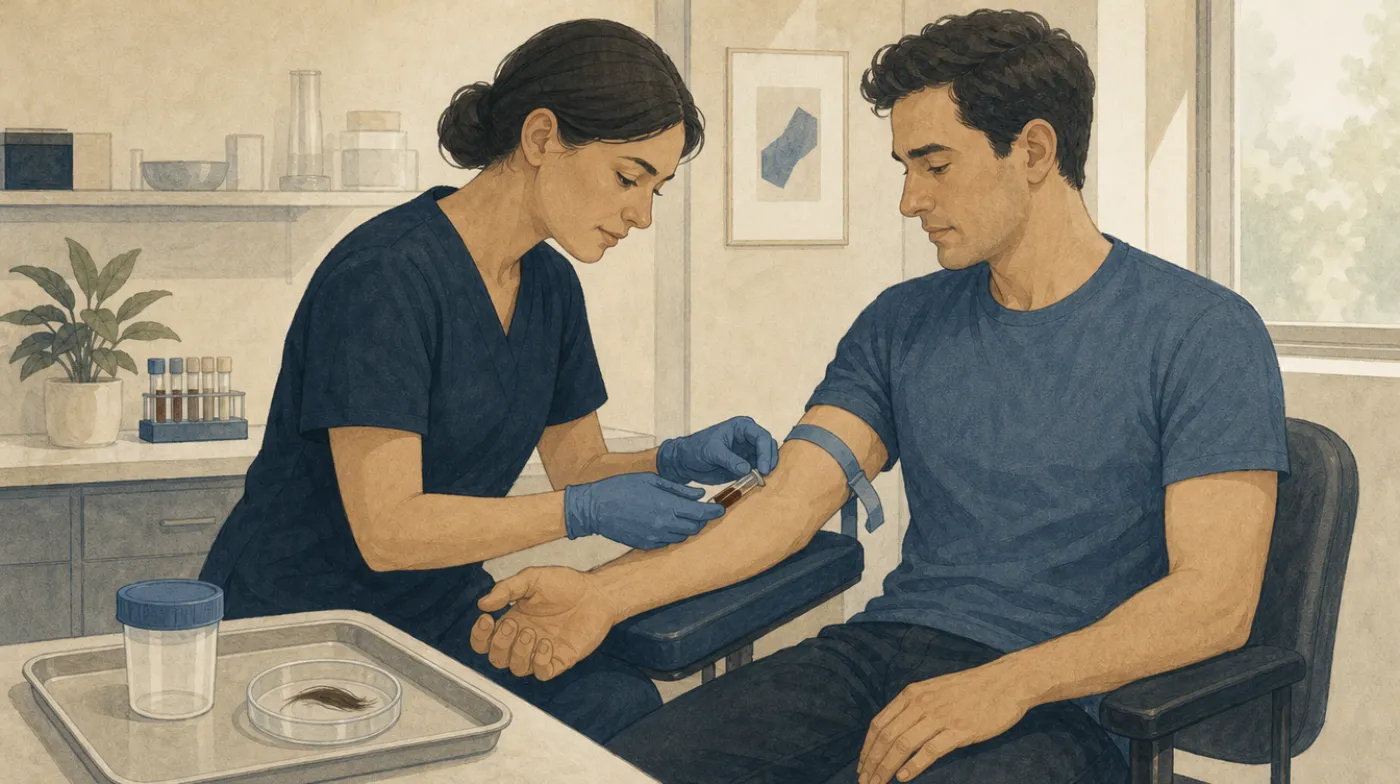
If you suspect heavy metal exposure, the first question you will face is: which test should I get? There are at least six different testing methods available, each measuring different things and suited for different metals. Choosing the wrong test can give you a false sense of security or, worse, an alarming result that does not reflect reality.
This matters because heavy metal testing drives treatment decisions. If a test says your mercury is elevated, you may be steered toward months of chelation therapy. If a test says your lead is normal when it is actually elevated, you may miss an exposure that is slowly damaging your cardiovascular system, kidneys, or brain. Getting the right test, from the right lab, interpreted by someone who understands the nuances, is the foundation of everything that follows.
Key Takeaways
- A whole blood lead test is the standard heavy metal blood test for lead, and the CDC blood lead reference value is 3.5 micrograms per deciliter (mcg/dL).
- Urine is more accurate than blood for arsenic and inorganic mercury, because both clear from the bloodstream quickly and leave the body through the kidneys.
- Hair tissue mineral analysis (HTMA) gave inconsistent results across six commercial labs testing identical samples, according to Seidel and colleagues in JAMA (2001).
- The American College of Medical Toxicology (2010) cautions against provoked urine testing judged against unprovoked reference ranges, because nearly everyone excretes more metal after a chelating agent.
- Trace element free collection tubes, ICP-MS analysis and outside proficiency testing, such as the CDC Lead and Multielement Proficiency program, are the quality controls that make a whole blood metals result trustworthy.
- An abnormal result should be repeated and matched to an exposure history before anyone starts chelation therapy.
At a Glance
- Whole blood testing is the gold standard for lead and is best for recent or ongoing exposure to most metals.
- Urine testing (spot or 24-hour) is the preferred method for mercury and arsenic.
- Hair mineral analysis can detect chronic, low-level exposure over months but has significant reliability concerns.
- Provocation (challenge) testing uses a chelating agent to mobilize metals from tissue, but results must be interpreted against provoked reference ranges, not standard ones.
- The best test depends on which metal you are testing for, whether the exposure is recent or chronic, and what clinical question you are trying to answer.
- Major reference labs (Quest Diagnostics, LabCorp) offer standard panels. Specialty labs (Doctor’s Data, Genova Diagnostics) offer more detailed profiles.
Understanding the Different Test Types
Heavy metal tests go by several names on a lab order: a heavy metals panel, a toxic metals panel, a toxic element profile, or a single analyte test such as a blood lead level (BLL). Each one is defined by two things, the specimen (whole blood, serum, urine or hair) and whether a chelating agent was given first. The sections below describe each specimen in turn.
Whole Blood Testing
A standard blood draw that measures metal concentrations in whole blood (both the plasma/serum and the cellular components). This is the most widely used and most standardized method for heavy metal testing.
What it measures: Metals circulating in the bloodstream at the time of the draw. This primarily reflects recent exposure (days to weeks) and ongoing chronic exposure. For lead specifically, blood levels reflect a combination of recent exposure and lead being released from bone stores.
Best for:
- Lead: Whole blood lead is the definitive test. The CDC reference value is 3.5 micrograms per deciliter (mcg/dL) for adults. Levels above 5 mcg/dL warrant investigation, and levels above 10 mcg/dL typically require intervention.
- Mercury (organic/methylmercury): Blood mercury is useful for assessing methylmercury exposure from fish consumption. Levels above 5 mcg/L suggest elevated exposure.
- Cadmium: Blood cadmium reflects recent exposure and is useful for monitoring occupational exposure. Non-smoker reference range is below 1 mcg/L.
Limitations: Blood testing may not capture metals stored in bones, organs, and soft tissues. Someone with a significant historical lead exposure could have a “normal” blood lead level because most of their lead burden has been deposited in bone. Blood testing also has a limited window for metals that are rapidly cleared from the blood (arsenic, for example, is mostly cleared within 24 to 48 hours).
Serum Testing
Serum testing measures metals only in the liquid portion of blood (after cells are removed by centrifugation). This is less commonly used than whole blood testing for most metals because many metals bind to red blood cells. Serum testing can underestimate true levels for metals like lead that are predominantly carried in red blood cells.
When it is used: Some specialty panels use serum for specific metals. Serum copper and serum zinc are common and clinically useful. For heavy metals specifically, whole blood is almost always preferred over serum.
Spot Urine Testing
A single urine sample collected at one point in time. Results are typically expressed as micrograms per liter (mcg/L) or normalized to creatinine concentration (mcg/g creatinine) to account for urine dilution.
Best for:
- Arsenic: Urine is the preferred specimen for arsenic testing. Spot urine arsenic above 50 mcg/L (or above 35 mcg/g creatinine) warrants follow-up. Note: seafood consumption within 48 hours can dramatically elevate urine arsenic due to organoarsenicals (non-toxic forms), so patients should avoid seafood for 48 hours before testing.
- Mercury (inorganic): Urine mercury primarily reflects inorganic mercury exposure (dental amalgams, occupational). Levels above 20 mcg/L are elevated.
- Thallium, cobalt, and other trace metals.
Limitations: Spot urine can vary significantly based on hydration status and time of day. Creatinine correction helps but does not completely solve this problem. For more accurate results, a first-morning void or a 24-hour collection is preferred.
24-Hour Urine Collection
The patient collects all urine produced over a full 24-hour period into a provided container. This eliminates the variability of spot urine testing and gives a more accurate picture of daily metal excretion.
Best for: Any metal where urine testing is preferred, particularly when spot urine results are borderline or inconsistent. Considered the most accurate urine-based method for mercury, arsenic, and cadmium.
Limitations: Patient compliance can be a challenge. Incomplete collections (missing voids during the 24-hour period) will underestimate true excretion. The collection container must be provided by the lab and is typically acid-washed to prevent contamination.
Hair Mineral Analysis
A sample of hair (typically 1 to 2 inches from the scalp, representing approximately 1 to 2 months of growth) is analyzed for mineral and metal content. Hair accumulates metals over time, so it provides a longer window of exposure than blood or urine.
Potential advantages:
- Non-invasive (no needles, no urine collection).
- Reflects chronic exposure over weeks to months.
- Can detect some metals (methylmercury, arsenic) that are rapidly cleared from blood and urine.
Significant concerns: Hair mineral analysis has substantial reliability problems. External contamination (shampoos, hair dyes, chlorinated water, environmental dust) can artificially elevate results. Different labs analyzing the same hair sample often produce different results. A 2001 study published in JAMA sent identical hair samples to six commercial labs and found large discrepancies in both measured values and clinical recommendations.1 The CDC and most toxicology organizations do not recommend hair analysis as a primary diagnostic tool for heavy metal exposure. It can be a useful screening tool in the right context, but results should always be confirmed with blood or urine testing before making treatment decisions.
Provocation (Challenge) Testing
Provocation testing involves administering a chelating agent (most commonly DMSA, sometimes EDTA or DMPS), then collecting urine for 6 to 24 hours to measure how much metal the chelator mobilizes from tissues.
The rationale: Standard blood and urine tests may miss metals that are stored in bones, organs, and deep tissues. A chelation challenge pulls these metals out, potentially revealing a body burden that baseline testing cannot detect.
The DMSA challenge protocol: The most common provocation protocol uses DMSA (dimercaptosuccinic acid, also known as succimer). A typical challenge involves administering 10 to 30 mg/kg of DMSA orally, then collecting all urine for 6 hours (some protocols use 24 hours). The urine is sent to a specialty lab for metals analysis. Baseline (pre-challenge) urine should also be collected for comparison.
The controversy: Provocation testing is the most debated method in heavy metal testing. The core problem is that everyone will excrete more metals after a chelation challenge, even healthy people with no significant metal exposure. If the provoked results are compared to unprovoked reference ranges (which they frequently are in some clinical settings), nearly everyone appears to have “elevated” metals.
Several medical organizations, including the American College of Medical Toxicology (ACMT), have issued position statements cautioning against provocation testing when results are compared to unprovoked reference ranges. They argue this practice leads to overdiagnosis and unnecessary treatment.2
That said, provocation testing can have clinical utility when:
- Results are compared to provoked reference ranges (some labs provide these).
- Pre-challenge and post-challenge results are compared to each other (looking at the ratio of increase).
- The test is used to monitor treatment progress (comparing provoked excretion before and after a course of chelation).
- There is a specific clinical reason to suspect deep tissue metal storage that baseline testing cannot capture.
Heavy Metal Testing Blood vs Urine: Which Is More Accurate?
Neither blood nor urine is more accurate for every metal. Whole blood is more accurate for lead, methylmercury from fish, and recent cadmium exposure, while urine is more accurate for arsenic, inorganic mercury, and long-term cadmium buildup in the kidneys. The right specimen is the one that matches where the body carries the metal and how fast it clears it.
When is a heavy metal blood test more accurate?
A blood test is more accurate when the metal binds to red blood cells and stays in circulation for weeks. Lead and methylmercury both behave this way, so a venous whole blood sample captures the current exposure well. Blood mercury from fish has a half-life of roughly 70 days, as the quick reference table below notes, which gives a useful window for testing.
When is a urine test more accurate?
A urine test is more accurate when the kidneys are the main route out of the body. Arsenic leaves the blood within about 24 to 48 hours and appears in urine, and inorganic mercury from amalgams or workplace vapor is excreted through the kidneys over months. A 24-hour collection is the most accurate urine method, and a first-morning spot sample corrected for creatinine is the practical alternative.
Why the answer depends on the metal and the timing
Timing changes the answer as much as the metal does. A blood sample taken days after a short arsenic or thallium exposure can look normal, and a blood lead test years after a heavy exposure can understate the lead held in bone. Toxicologists at the Agency for Toxic Substances and Disease Registry (ATSDR) describe a preferred biomarker for each metal in their toxicological profiles for that reason.
| Specimen | What it reflects | Most reliable for | Main weakness |
|---|---|---|---|
| Whole blood | Metal in circulation now, from recent and ongoing exposure | Lead, methylmercury, recent cadmium | Misses metal already stored in bone and tissue |
| Spot urine | Metal the kidneys are excreting at one point in time | Arsenic, inorganic mercury, thallium | Shifts with hydration and recent meals, especially seafood |
| 24-hour urine | Total daily excretion | Mercury, arsenic, cadmium when spot results are borderline | Incomplete collections understate excretion |
| Hair (HTMA) | Metal laid down in hair over one to two months | Methylmercury in research settings | External contamination and poor agreement between labs |
| Provoked urine | Metal pulled out by a chelating agent | Monitoring a chelation course against its own baseline | Inflated results when compared to unprovoked ranges |
Hair Tissue Mineral Analysis vs Other Diagnostic Testing Options
Hair tissue mineral analysis (HTMA) differs from blood and urine testing in three ways: it reflects months rather than days, it can be contaminated from the outside of the hair shaft, and it has no standardized reference ranges that labs share. Blood and urine tests measure what is inside the body at the time of collection and are run under federal laboratory rules with outside proficiency checks. That difference is why toxicologists treat HTMA as a screening tool at most.
What does hair analysis measure well?
Hair is a reasonable record of methylmercury, the form of mercury in fish, because methylmercury binds to the proteins in growing hair. Researchers use hair mercury in population studies of fish consumption for that reason. For lead, cadmium, aluminum and most other metals, hair levels track poorly with what is in blood and tissue.
Why do HTMA results differ between labs?
HTMA results differ because labs use different washing steps, cutting lengths and reference ranges. In the study by Seidel and colleagues in JAMA (2001), identical hair samples sent to six commercial labs came back with conflicting metal levels and conflicting supplement advice. Shampoos, dyes, pool water and dust add metal to the outside of the hair, and washing cannot reliably separate that from metal inside it.
How HTMA compares with other diagnostic tests
- HTMA vs a heavy metal blood test: a blood test is the standard for lead and recent exposure, and HTMA cannot replace it.
- HTMA vs urine metals testing: urine is the accepted specimen for arsenic and inorganic mercury, and it reflects what the kidneys are clearing now.
- HTMA vs provoked urine testing: both are debated, for different reasons; HTMA for contamination and lab variability, provoked urine for inflated comparisons.
- HTMA vs bone lead measurement: K-shell X-ray fluorescence (KXRF) measures lead stored in bone directly, but it is a research tool found in a few university settings.
A hair result that suggests a problem is a reason to order a blood or urine test, not a reason to start treatment. Clinicians who order HTMA in functional and integrative medicine practices generally use it the same way.
Which Metal, Which Test: A Quick Reference
| Metal | Best Primary Test | Useful Secondary Test | Notes |
|---|---|---|---|
| Lead | Whole blood | Provoked urine (for bone stores) | Blood lead is the definitive test. ZPP (zinc protoporphyrin) can confirm chronic exposure. |
| Mercury (organic/methyl) | Whole blood | Hair (if recent fish exposure suspected) | Blood mercury reflects methylmercury from fish. Half-life is approximately 70 days. |
| Mercury (inorganic) | Urine (spot or 24-hour) | Provoked urine | Urine mercury reflects inorganic sources (amalgams, occupational). Avoid seafood 48 hours before testing. |
| Arsenic | Urine (spot or 24-hour) | Hair (for chronic exposure) | Avoid seafood 48 hours before testing. Speciated arsenic testing distinguishes toxic from non-toxic forms. |
| Cadmium | Whole blood (recent exposure) | Urine (chronic exposure) | Blood cadmium reflects recent exposure. Urine cadmium reflects long-term kidney accumulation. |
| Thallium | Urine | Whole blood | Urine is more sensitive than blood for thallium. |
| Aluminum | Serum or urine | Provoked urine | Contamination during collection is a significant concern. Use trace-element-free tubes. |
Interpreting Your Results
Getting a number on a lab report is only half the picture. Interpretation requires understanding what the numbers mean in context.
Reference Ranges vs. Optimal Levels
Lab reference ranges represent the statistical range found in the general population (typically the 95th percentile). For toxic metals, the reference range is not the same as a “safe” level. Lead, for example, has no known safe level. A blood lead of 2 mcg/dL is within the “reference range” but still represents lead exposure that ideally would not be present.
Some functional medicine practitioners use tighter “optimal” ranges that reflect minimal exposure. This approach has some clinical merit (particularly for lead and mercury, where even low levels are associated with health effects) but can also lead to over-treatment if results are only slightly above the optimal threshold.
The 3.5 mcg/dL blood lead figure is a reference value, not a health threshold. According to the CDC National Institute for Occupational Safety and Health blood lead guidance, the Council of State and Territorial Epidemiologists set 3.5 mcg/dL to flag adults and children whose levels sit above the 97.5th percentile nationwide. A result above it means more lead than most people carry, which is a prompt to find the source.
Common Pitfalls in Interpretation
- Comparing provoked to unprovoked ranges: As discussed above, this inflates apparent metal levels. Always confirm which reference range is being used.
- Ignoring seafood effects on arsenic and mercury: A patient who ate sushi the day before testing may show elevated arsenic and mercury that reflect harmless organic forms, not toxic exposure. Speciated arsenic testing and a 48-hour seafood avoidance window eliminate this confounding factor.
- Single-test diagnosis: One elevated result should be confirmed with a repeat test before initiating treatment. Lab error, contamination, and transient exposure can all produce a single abnormal result that does not reflect chronic toxicity.
- Ignoring the clinical picture: Metal levels should be interpreted alongside symptoms, exposure history, and other lab findings. A mildly elevated lead level in someone with hypertension, chronic kidney disease, and a history of working in a battery factory tells a very different story than the same level in a healthy patient with no identifiable exposure.
Whole Blood Metals Quality Control: How Labs Keep Results Accurate
Whole blood metals quality control is the set of checks that keeps a lab's lead, mercury and cadmium results accurate: trace element free collection tubes, calibrated ICP-MS instruments, blank and control samples in every run, and outside proficiency testing. Errors at low concentrations are common without these controls, as Caldwell and colleagues at the CDC described in Pediatrics (2017). A result is only as reliable as the weakest step between the needle and the report.
What quality checks happen inside the lab?
Labs measure toxic metals with inductively coupled plasma mass spectrometry (ICP-MS), which can detect metals at very low concentrations. Each batch runs alongside reagent blanks, which catch metal leaching from tubes and reagents, and control blood with known values, which confirms the instrument is reading correctly. Many labs also calibrate against certified reference materials from the National Institute of Standards and Technology (NIST).
What outside oversight applies?
Clinical labs in the United States operate under the Clinical Laboratory Improvement Amendments (CLIA), which the Centers for Medicare and Medicaid Services (CMS) administers, and blood lead is a regulated analyte with required proficiency testing. The CDC Lead and Multielement Proficiency (LAMP) program sends participating labs blood samples each quarter and reports back on their accuracy for lead, cadmium and mercury. Accreditation from the College of American Pathologists (CAP) adds another layer of inspection.
Questions to ask before you test
- Is the lab CLIA certified, and does it take part in proficiency testing for the metals on the panel?
- Will the sample be drawn into a trace element free tube, usually a royal blue top?
- Is the test a venous draw, or a finger-stick sample that may need confirming?
- Which reference range is printed on the report, and was it built from unprovoked samples?
When to Get Tested
Not everyone needs heavy metal testing. It is most appropriate when there is a clinical reason to suspect exposure. Consider testing if you have:
- Known or suspected exposure: Living near industrial sites, working in mining/smelting/manufacturing, old home with lead paint, well water in areas with arsenic contamination, multiple dental amalgam fillings, frequent consumption of high-mercury fish.
- Unexplained neurological symptoms: Peripheral neuropathy, cognitive changes, tremor, mood disturbances without clear cause.
- Unexplained kidney disease: Chronic kidney disease without clear etiology (lead and cadmium are significant nephrotoxins).
- Cardiovascular disease with environmental risk factors: Given TACT trial data, metal burden assessment may be relevant for post-MI patients, particularly those with diabetes.
- Chronic fatigue or autoimmune conditions: While metals are not always the cause, they can contribute to immune dysregulation and mitochondrial dysfunction.
- Children with developmental delays: Lead screening is particularly important in children, where even low levels can affect neurodevelopment.
Symptoms alone rarely point to one metal. Fatigue, brain fog and joint pain overlap with conditions such as chronic fatigue syndrome and toxic mold exposure, so a clear exposure history is what makes a heavy metal test worth ordering. The early signs of lead in particular are covered in lead poisoning symptoms in adults and children.
Who Orders and Interprets Heavy Metal Tests?
Primary care physicians and pediatricians order most heavy metal blood tests, usually a blood lead level. Medical toxicologists and occupational medicine physicians handle confirmed or work-related exposures, and nephrologists and neurologists order metal testing when kidney disease or neuropathy has no clear cause. Integrative, functional medicine and naturopathic clinicians often order expanded panels from specialty labs.
For a suspected acute poisoning, Poison Control in the United States answers at 1-800-222-1222 and can connect callers with a toxicologist. Employers whose workers are exposed to airborne lead above the action level must offer blood lead monitoring under the Occupational Safety and Health Administration (OSHA) lead standards. Public health departments follow up on elevated blood lead reports in children.
Finding a Qualified Lab
The lab you choose matters. Heavy metal testing requires specialized analytical equipment (typically ICP-MS, or inductively coupled plasma mass spectrometry) and strict contamination controls.
| Lab | Type | Strengths | Availability |
|---|---|---|---|
| Quest Diagnostics | Reference lab | Widely available, insurance-accepted, standardized panels | Nationwide (US) |
| LabCorp | Reference lab | Wide availability, standard and specialty panels | Nationwide (US) |
| Doctor’s Data | Specialty lab | Detailed metal panels, provoked urine expertise, hair analysis | By clinician order |
| Genova Diagnostics | Specialty lab | Toxic element profiles, comprehensive panels, functional medicine focus | By clinician order |
| Great Plains Laboratory (Mosaic Diagnostics) | Specialty lab | GPL-TOX panel (metals + environmental toxins), mycotoxin testing | By clinician order |
Practical tip: For an initial screen, Quest or LabCorp offer standard heavy metal panels that are affordable ($100 to $300), widely available, and often partially covered by insurance. If results are borderline or if you need more detailed analysis, specialty labs like Doctor’s Data or Genova offer expanded panels with more metals tested and lower detection limits. Specialty labs typically require a clinician order and are out-of-pocket ($200 to $500 for detailed panels).
Can You Do a Heavy Metal Test at Home?
At-home heavy metal test kits exist in three forms: finger-stick blood spots, urine cups and hair samples mailed to a lab. A finger-stick blood lead result can read high because lead on the skin gets into the drop, and CDC guidance is that an elevated capillary result be confirmed with a venous blood draw. Home hair kits carry the same contamination and lab variability problems as any HTMA.
A home kit can be a starting point when the lab behind it is CLIA certified and the report states its specimen and reference range. A clinician should repeat any abnormal home result with a standard venous or urine test before treatment is discussed.
False Positives and Common Mistakes
Heavy metal testing is prone to several sources of error that can produce misleading results:
- Contamination during collection: Standard blood draw tubes (red top, green top) may contain trace metals that leach into the sample. Heavy metal testing requires special trace-element-free tubes (royal blue top, typically). If your blood is drawn into a standard tube, results may be falsely elevated.
- Seafood confounding: As noted, seafood within 48 hours elevates arsenic and mercury. Always disclose seafood intake to your provider and the lab.
- External contamination of hair samples: Hair dyes, certain shampoos, chlorinated pool water, and environmental dust can all affect hair mineral analysis results.
- Supplement interference: Some supplements (particularly those containing kelp, spirulina, or other seaweed products) contain arsenic. Herbal preparations may contain lead or mercury depending on their source.
- Timing of sample: For metals with short blood half-lives (arsenic, thallium), a blood sample taken more than 24 to 48 hours after exposure may appear normal despite significant recent exposure.
Building a Testing Strategy
Rather than ordering every available test, a targeted approach works best:
- Start with baseline blood and urine. A whole blood metals panel plus a spot urine metals panel covers the most common toxic metals through the most reliable methods. Cost: $150 to $400 total through Quest or LabCorp.
- Speciate arsenic if elevated. If total arsenic is high, speciated arsenic testing distinguishes toxic inorganic arsenic from harmless organoarsenicals. This avoids unnecessary alarm from seafood-related elevation.
- Add 24-hour urine if spot results are borderline. A 24-hour collection provides more accurate results than a spot sample and can clarify equivocal findings.
- Consider provocation testing selectively. If baseline testing is normal but clinical suspicion remains high (strong exposure history, symptoms consistent with metal toxicity), a supervised DMSA challenge with proper provoked reference ranges can assess tissue burden. This should be ordered and interpreted by a provider experienced in toxicology.
- Retest before treating. Always confirm an abnormal result with a second test before committing to a chelation course. The cost of retesting ($100 to $300) is far less than the cost of unnecessary treatment.
For information on treatment options if testing reveals elevated metal levels, see our guides to chelation therapy and DMSA chelation.
What Happens After an Abnormal Heavy Metal Test?
The first step after a confirmed abnormal result is finding and removing the source of exposure, which lowers blood levels for many people without any drug. Common sources include old paint and dust, workplace fumes, private well water, imported spices and cosmetics, and some herbal products. A repeat test after the source is removed shows whether levels are falling.
Chelation therapy is the drug treatment for heavy metal poisoning. The FDA has approved oral succimer (DMSA) for lead poisoning in children and intravenous calcium disodium EDTA for lead poisoning, and these are used under the supervision of physicians experienced with them. The chelation therapy treatment guide covers the agents, and the lead poisoning condition page covers how clinicians decide when chelation is indicated.
Evidence is thin for chelation outside documented poisoning. Many clinics offer IV chelation for fatigue, heart disease or a provoked urine result, usually as a cash pay service and off label. The chelation therapy guide and the evidence review on heavy metal detox set out what the research does and does not support.
To compare providers, you can browse chelation therapy clinics by location in the directory and check which clinics list toxic exposure care alongside it. Regenerated.com is free for patients, listing order is not paid ranking, Featured slots are labeled and capped, and Verified means credential checks, not spend. Inclusion in the directory is not an endorsement, so ask any clinic which tests it uses and which reference ranges it reads them against.
Frequently asked questions
Is blood or urine more accurate for heavy metal testing?
Blood is more accurate for lead, methylmercury from fish and recent cadmium exposure, while urine is more accurate for arsenic, inorganic mercury and long-term cadmium. The difference comes from how each metal moves through the body: lead and methylmercury stay in red blood cells for weeks, while arsenic leaves the blood within about two days and is excreted in urine. A 24-hour urine collection is the most accurate urine method when a spot result is borderline.
What's the difference between hair tissue mineral analysis and other diagnostic testing options?
Hair tissue mineral analysis measures metal laid down in hair over one to two months, while blood and urine tests measure what is in the body at the time of collection. Hair can be contaminated from the outside by dyes, shampoo and dust, and a JAMA study (Seidel, 2001) found six labs gave conflicting results on identical samples. Blood and urine tests run under CLIA rules with proficiency testing, so they are the tests used to confirm a diagnosis.
What does a heavy metal blood test check for?
A heavy metal blood test, ordered as a whole blood metals panel, usually measures lead and mercury, and often arsenic and cadmium as well. A standalone blood lead level is the most common single test. Blood results reflect recent and ongoing exposure, so they may understate lead stored in bone. The sample should be drawn into a trace element free tube, usually a royal blue top, to avoid contamination.
Should I do a provoked urine test before chelation?
A provoked urine test is only meaningful when it is compared with provoked reference ranges or with your own pre-challenge sample. The American College of Medical Toxicology (2010) cautions against reading provoked results against ordinary ranges, because nearly everyone excretes more metal after a chelating agent such as DMSA. Most toxicologists start with unprovoked blood and urine testing and confirm any abnormal result before chelation is considered.
How should I prepare for a heavy metal test?
Avoid fish and shellfish for 48 hours before a urine or blood test for arsenic or mercury, because seafood raises levels with forms that are mostly harmless. Tell the clinician about supplements such as kelp or spirulina and any herbal products. For a 24-hour urine test, use only the acid-washed container from the lab and collect every void. Ask that blood be drawn into a trace element free tube.
Does insurance cover heavy metal testing?
Insurance often covers standard heavy metal panels from reference labs such as Quest Diagnostics and LabCorp when a clinician orders them for a documented exposure or symptoms. Blood lead screening in children is widely covered. Expanded panels from specialty labs, hair analysis and provoked urine tests are usually paid out of pocket. The Finding a Qualified Lab section above lists the typical price ranges for each type of panel.
Sources
- Seidel S, Kreutzer R, Smith D, McNeel S, Gilliss D. Assessment of commercial laboratories performing hair mineral analysis. JAMA. 2001;285(1):67-72. doi:10.1001/jama.285.1.67 ↩
- American College of Medical Toxicology. Position statement on post-chelator challenge urinary metal testing. J Med Toxicol. 2010;6(1):74-75. doi:10.1007/s13181-010-0039-0 ↩
- Caldwell KL, Cheng PY, Jarrett JM, et al. Measurement challenges at low blood lead levels. Pediatrics. 2017;140(2):e20170272. doi:10.1542/peds.2017-0272
- Kales SN, Goldman RH. Mercury exposure: current concepts, controversies, and a clinic’s experience. J Occup Environ Med. 2002;44(2):143-154. doi:10.1097/00043764-200202000-00009
- Agency for Toxic Substances and Disease Registry (ATSDR). Toxicological profiles for lead, mercury, arsenic, and cadmium. Atlanta, GA: U.S. Department of Health and Human Services.
- Navas-Acien A, Guallar E, Silbergeld EK, Rothenberg SJ. Lead exposure and cardiovascular disease: a systematic review. Environ Health Perspect. 2007;115(3):472-482. doi:10.1289/ehp.9785
- Centers for Disease Control and Prevention. Lead and Multielement Proficiency Program (LAMP). Laboratory Quality Assurance and Standardization Programs. https://www.cdc.gov/laboratory-quality-assurance/php/inorganic-elements/lamp.html
- National Institute for Occupational Safety and Health. Blood Lead Level Guidance. https://www.cdc.gov/niosh/lead/bll-reference/index.html


